Relative vs Absolute Risk: What “50% Higher Risk” Really Means
A headline says a food raises your risk by 50%. Should you worry? Relative vs absolute risk, a pill scare that backfired, and the one question to ask.
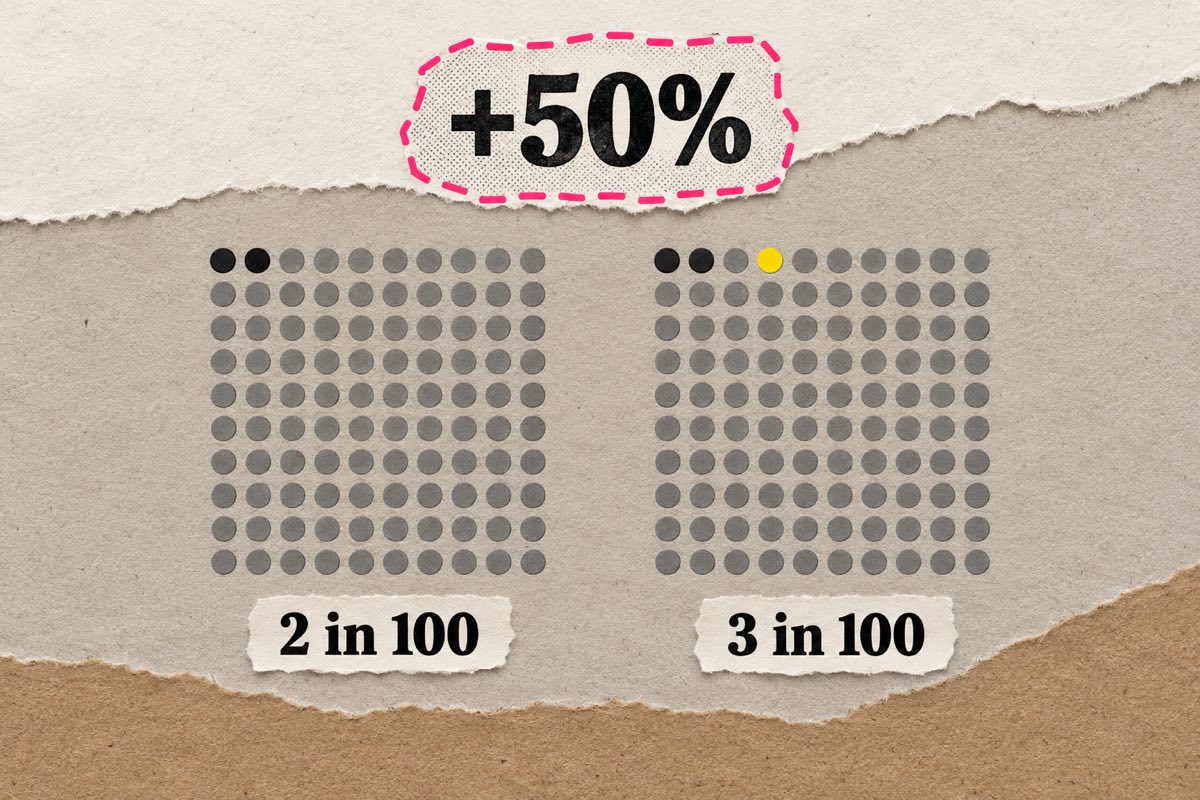
“Eating X raises your risk of Y by 50%.”
It’s a line you’ve read in some form, many times, and it sounds alarming. Whether it is alarming depends entirely on a number that the headline almost never includes.
Try it
What does “50% higher risk” look like?
Set the usual risk, then how much a headline says it rises. Each dot is one person in 1,000.
A 50% rise takes the risk from 2 in 1,000 to 3.0 in 1,000: 1.0 extra person per 1,000. The headline says “50% higher”; the change in your risk is 0.10 percentage points.
Two ways to describe the same change
Suppose your risk of some illness is 2 in 10,000, and a food raises it to 3 in 10,000.
- Relative risk: the risk went from 2 to 3, a rise of 50%.
- Absolute risk: the risk went up by 1 in 10,000, or 0.01 percentage points.
Both statements are true. They just answer different questions. The relative figure tells you how much bigger the risk became compared with before. The absolute figure tells you how much your actual chances changed.
For a decision, you almost always want the second. Whether to give up a food depends on how much your real risk moves, and a 50% rise in a very rare event barely moves it.
Why headlines prefer relative risk
Relative numbers are bigger and more dramatic. “Doubles your risk” is a better headline than “raises your risk from 1 in 50,000 to 2 in 50,000”. Press releases, adverts for treatments and even some scientific papers lean on relative figures for exactly this reason.
It works in both directions. A drug that “cuts heart attacks by 30%” may take the risk from 10 in 1,000 to 7 in 1,000: three people in a thousand helped. The advert sounds like a rescue. The reality is that for 997 out of 1,000 people who take it, the outcome is the same either way.
The same relative number can describe very different situations:
| Starting risk | A “50% rise” takes it to | Extra people per 1,000 |
|---|---|---|
| 1 in 10,000 | 1.5 in 10,000 | 0.05 |
| 2 in 1,000 | 3 in 1,000 | 1 |
| 1 in 100 | 1.5 in 100 | 5 |
| 1 in 10 | 1.5 in 10 | 50 |
The headline is identical in all four. The human consequence differs a thousandfold.
The one question to ask
Whenever you see a percentage rise or fall in risk, ask:
50% of what?
If the starting risk is tiny, even a big relative rise leaves it tiny. If the starting risk is large, a small relative change can matter a great deal. The toy at the top shows it: set a starting risk and a headline’s rise, and see the extra people in a crowd of 1,000.
Number needed to treat
Doctors use a figure that turns an absolute change into people: the number needed to treat, or NNT. If a treatment takes the risk of something from 10 in 1,000 to 7 in 1,000, it prevents 3 cases for every 1,000 people treated. So about 333 people have to take it for one of them to benefit.
Try it
From a headline to people helped
A drug advert says it “cuts your risk by” some percentage. Set how common the problem is without the drug, and the cut it promises, and see how many people it actually helps.
The advert says “30% lower risk”. In real terms that’s 3.0 people helped for every 1,000 treated: you’d treat about 333 people to help one. Try a bigger starting risk and the same “30%” suddenly helps far more people.
These numbers make trade-offs visible. A treatment that helps 1 in 333 might be well worth it if it’s cheap and safe, and not worth it if it has serious side effects. Equally, there’s a number needed to harm: how many people take it for one to be hurt. A good decision weighs the two, and you can’t see either from the relative figure alone.
A scare that cost thousands of unplanned pregnancies
In October 1995, the UK’s Committee on Safety of Medicines sent a warning to doctors: new “third-generation” contraceptive pills were linked to double the risk of blood clots in the veins, compared with older ones. It was reported on the news that day. “Doubled” sounded terrifying.
The absolute numbers were different. In women on the older pills, about 1 in 7,000 would have a clot in a year. On the newer pills, that rose to about 2 in 7,000. One extra woman in 7,000. The risk of clots in pregnancy, by comparison, is considerably higher than on either pill.
Many women stopped taking the pill. In the following year, England and Wales saw an estimated 13,000 additional abortions and a rise in unplanned pregnancies, with their own risks, including a higher rate of clots. A relative risk, reported without its denominator, may have done real harm.
Try it
The 1995 pill scare
In 1995 the UK’s drug safety authority warned that newer contraceptive pills “doubled” the risk of dangerous blood clots. Before the newer pills, about 1 woman in 7,000 per year had one. What did the “doubling” mean for a woman on the newer pill?
Pick one. You’ll see why straight after.
A calmer example: processed meat
In 2015, the World Health Organization’s cancer agency announced that processed meat causes bowel cancer. The figure that went round the world was that eating 50 grams a day, about two slices of bacon, raises the risk by 18%.
That’s a relative figure. The absolute picture depends on the starting point. A typical person in the UK has a lifetime risk of bowel cancer of around 6 in 100. An 18% rise takes it to about 7 in 100: roughly one extra case in every hundred people who eat that much every day for life.
It’s a real effect, and it deserves to be taken seriously, and it’s also very different from the way it was often reported. An accurate summary might be: “eating bacon every day may take your lifetime risk of bowel cancer from about 6% to about 7%.” You can decide what to make of that. But you can only decide once you’ve seen it.
Risk in the other direction
The same logic applies to benefits, and it’s used in advertising for medicines. The Women’s Health Initiative trial, which tested hormone therapy, found 38 breast cancers per 10,000 women a year on the hormones against 30 on the placebo. In relative terms, a 26% increase. In absolute terms, 8 more women in 10,000 in a year.
Neither framing is dishonest. But each tells a different story to a different reader, and you’ll usually see only the one that suits the person presenting.
How to read any risk headline
You don’t need statistics to protect yourself. You need three questions, asked in this order:
- What was the risk to start with? As people out of a thousand, or out of ten thousand. If the article doesn’t say, the number is probably small.
- What is it after? The same units. The difference is the absolute change.
- Over what period? A 1% risk in a year is very different from a 1% risk over a lifetime.
Then do the translation yourself: “out of 1,000 people like me, how many does this affect?” The shape of the answer is usually far less frightening, or far less impressive, than the headline.
How to say it better
If you write about health, or just pass on what you’ve read to friends, you can be fair in one sentence. Instead of “doubles your risk”, try “raises your risk from about 1 in 7,000 to about 2 in 7,000”. Instead of “cuts heart attacks by 30%”, “means 3 fewer heart attacks for every 1,000 people who take it”. It’s no harder to say, it’s harder to misread, and it lets the listener decide whether it matters to them.
Some journalists and doctors now do this routinely. Risk communicators call it using natural frequencies and absolute risks, and in studies it makes patients’ decisions noticeably better informed. It doesn’t reduce the importance of the finding. It just removes the fog.
What it doesn’t mean
None of this means small risks never matter. A one-in-a-thousand risk of something catastrophic is worth avoiding if avoiding it is cheap. A small absolute risk applied to millions of people is a big public-health problem. Relative risks matter in their own right, too, because they’re often what scientists need for working out causes.
The point is only that a single figure is never enough. Relative risk tells you the direction and rough size of an effect. Absolute risk tells you what it means for a person. You need both, and when only one is offered, you now know which one to ask for.
If you want to practise, the free probability test has a risk-headline question, and why a positive test often isn’t what it seems covers the related trap of forgetting how common something is to start with.
Questions people ask
- What is the difference between relative risk and absolute risk?
- Relative risk compares two risks as a ratio, such as “50% higher”. Absolute risk is the actual chance of something happening, such as 3 in 10,000. A headline giving only the relative change can make a tiny change in absolute risk sound huge.
- Why do headlines use relative risk?
- Because relative figures are bigger and sound more dramatic. “Doubles your risk” is a better headline than “raises your risk from one in 50,000 to two in 50,000”. Press releases and drug adverts do the same with reductions, such as “cuts heart attacks by 30%”.
- What is number needed to treat?
- The number of people who’d need to take a treatment for one of them to benefit. If a drug takes a risk from 10 in 1,000 to 7 in 1,000, it helps 3 in every 1,000 treated, so you’d treat about 333 people to help one. It makes the size of a benefit concrete.
- Did processed meat really cause that much cancer?
- In 2015 the WHO’s cancer agency classed processed meat as a cause of bowel cancer, and found that 50 grams a day raises the risk by about 18% in relative terms. For a typical person, whose lifetime risk is around 6 in 100, that’s roughly one extra case in 100 people who eat it every day. It’s real and modest.
- How can I check a health claim quickly?
- Ask three things. What was the risk to start with, as people out of a thousand? What is it afterwards? And over what period? If the article doesn’t say, treat the relative figure as incomplete and be wary of acting on it.
Sources and further reading
- Gigerenzer, G. (2002). Calculated Risks: How to Know When Numbers Deceive You. Simon & Schuster.
- Gigerenzer, G., Gaissmaier, W., Kurz-Milcke, E., Schwartz, L. M. and Woloshin, S. (2007). Helping doctors and patients make sense of health statistics. Psychological Science in the Public Interest, 8(2), 53–96.
- Bouvard, V. et al. (2015). Carcinogenicity of consumption of red and processed meat. The Lancet Oncology, 16(16), 1599–1600.
- Furedi, A. (1999). The public health implications of the 1995 ‘pill scare’. Human Reproduction Update, 5(6), 621–626.
- Writing Group for the Women’s Health Initiative Investigators (2002). Risks and benefits of estrogen plus progestin in healthy postmenopausal women. JAMA, 288(3), 321–333.
- Cancer Research UK. Bowel cancer risk statistics.